BLOG
Pelvic Girdle Pain (PGP) in Pregnancy: What Helps, and When Should You See a Physio?
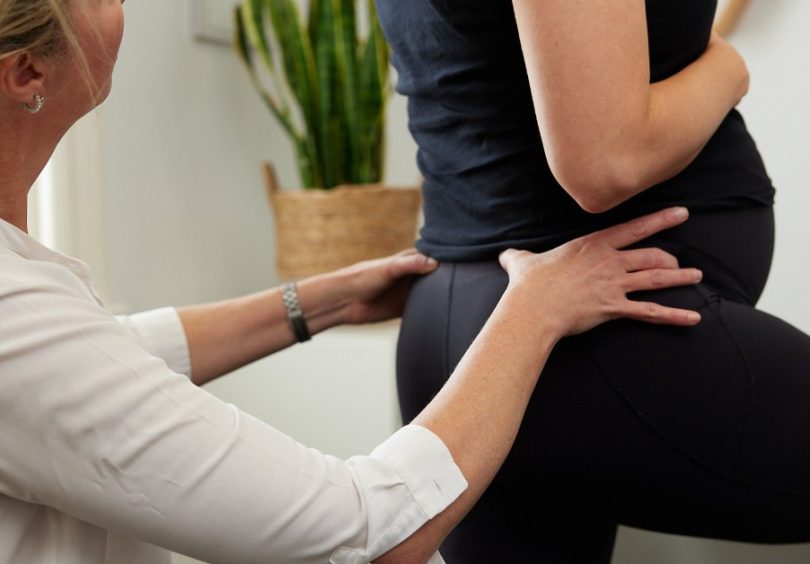

By Rebecca Wilson, Senior Physiotherapist, Malvern Physiotherapy Clinic
Pelvic girdle pain in pregnancy (PGP) is pain at the front or back of the pelvis that often flares with daily tasks such as walking, stairs, rolling in bed or getting dressed. It is common, not harmful to your baby, and physiotherapy at Malvern Physiotherapy Clinic may help you manage it.
If getting out of the car or turning over at night has started to make you wince, you are not alone. PGP is one of the most common reasons pregnant women come to see me, and our pregnancy and post-natal physiotherapy team at our Malvern East clinic sees it often.
Pelvic girdle pain is pain in the joints and tissues of the pelvis that develops during pregnancy (or occasionally after birth). The joints involved are the sacroiliac joints at the back of the pelvis, the pubic symphysis at the front, or both. That’s why some women feel it over the pubic bone, some in the lower back and buttocks, and some in both places.
You may hear it called sacroiliac joint pain (SIJ pain), pelvic instability or pubic symphysis dysfunction.
According to the Royal College of Obstetricians and Gynaecologists, it affects up to 1 in 5 pregnant women to some degree.
Symptoms range from mild discomfort to severe pain, and can spread to the lower back, pubic bone, buttocks, hips and thighs.
The pain is usually linked to movement. Common triggers include:
The exact cause isn’t fully understood. We do know the cause is multifactorial and likely involves a mix of biological, psychological and social factors.
During pregnancy there are physical changes. As your bump grows, you carry more weight at the front of your body, which changes your centre of gravity and therefore posture. However, this has not been proven to be linked with PGP.
A sore pelvis is not a sign that your pelvis is “coming apart” or “out of place”. The pain reflects tissue sensitivity, due to hormonal changes, genetic factors changing load around the joints and well-meaning but often negative messaging about exercise and the safety of movement in pregnancy.
You are more likely to have PGP if you:
No. PGP is not dangerous for you or your baby. It can still make daily life tiring. An Australian study cited in the Australian Journal of General Practice found that only 25% of women who reported PGP were offered any treatment, so it is worth getting help rather than waiting it out.
A pregnancy physiotherapist can confirm whether your pain is coming from the pelvic joints, then build a plan to make daily tasks easier and calm things down. Your physiotherapist will assess how you move, which activities provoke your pain, and the strength of the muscles around your hips, pelvis and trunk.
Depending on what we find, treatment often includes:
Some women also add myotherapy during pregnancy with our myotherapy team. Pregnant and post-natal clients are also welcome in our Clinical Pilates classes, following a Clinical Pilates assessment, as a supervised way to build strength.
Treatment recommendations will depend on your individual presentation. For a broader picture, see how physiotherapy can support you through pregnancy and postnatal recovery.
Small changes to everyday movements often help most. The aim is to avoid single-legged loading of the pelvis and keep moving within comfortable limits.
| Everyday task | What tends to aggravate PGP | What may help |
|---|---|---|
| Getting dressed | Standing on one leg | Sit down to put on pants, socks and shoes |
| Stairs | Taking stairs often or two at a time | Go one step at a time, stepping up with the less sore leg first |
| Turning in bed | Twisting with your knees apart | Keep your knees together and roll as one unit; sleep with a pillow between your knees |
| Getting out of the car | Swinging one leg out at a time | Sit first, then turn both legs together |
| Walking and standing | Long walks or standing for long periods | Shorter walks, smaller steps, sit to rest more often |
| Lifting | Carrying a toddler or shopping on one hip | Share the load, use a trolley, ask your toddler to climb onto a chair to be picked up |
Gentle exercise is generally encouraged, and mild discomfort that settles quickly is usually OK. If an exercise causes sharp or lingering pain, stop and check with your physiotherapist. Our guide to exercising safely during pregnancy covers this in more detail.
See a physiotherapist as soon as pelvic pain is making daily tasks harder.
Consider booking an assessment if:
A thorough assessment is important to determine the most appropriate treatment approach. You do not need a referral to see a physiotherapist, but please keep your midwife or obstetrician informed.
Some symptoms are not PGP and need urgent review by your midwife, doctor or maternity hospital. The Royal Women’s Hospital advises coming into hospital if you have any of the following:
The Royal Women’s Hospital also advises coming into hospital if you have irregular contractions, your waters break, you have sharp abdominal pain, or you have pain or burning when you pass urine. In an emergency, call 000.
For most women, yes. The AJGP review reports that 93% of women had their symptoms settle within three months of birth. A smaller number have pain that lingers, and PGP can come back in a later pregnancy.
If pain continues after your baby arrives, a postnatal physiotherapy review is worthwhile, and a good time to check your pelvic floor (see our post on pelvic floor problems). Some women also find post-natal myotherapy helpful for tension from feeding and carrying.
They overlap. Pubic symphysis dysfunction (PSD) usually refers to pain at the front of the pelvis over the pubic bone, while pelvic girdle pain (PGP) is the broader, umbrella term that also covers pain at the back of the pelvis. The advice and treatment are much the same.
It can happen at any time, but usually starts between 14 and 30 weeks, and it can continue after the baby is born.
Usually, yes, with some modifications. Gentle activity within comfortable limits is generally encouraged. Exercises that put weight through one leg (e.g. lunges) may need adjusting. Your physiotherapist will assess you and suggest exercises that suit your stage of pregnancy.
They can help some women. A pelvic support belt, tape or compression garment may reduce pain when it is fitted correctly. They are usually used alongside exercise rather than instead of it. Your physiotherapist can advise whether one suits you.
Most women with PGP can have a vaginal birth. It is worth mentioning your PGP in your birth plan and discussing pain relief options and comfortable birth positions with your birthing team.
It may. Having PGP before makes it more likely to happen again. Seeing a physiotherapist early in your next pregnancy can help you plan ahead. Regular exercise and keeping your abdominal and pelvic floor muscles strong may reduce your chances.
If pelvic girdle pain is making your pregnancy harder, an assessment can help you understand what is going on and what may help.
Book online at malvernphysio.janeapp.com or call our team on (03) 9078 8434. Malvern Physiotherapy Clinic is at 299 Wattletree Road, Malvern East VIC 3145, convenient to Malvern, Armadale, Toorak, Glen Iris and the wider Stonnington area. No referral is needed.
Rebecca Wilson is a Senior Physiotherapist at Malvern Physiotherapy Clinic. She holds a Bachelor of Applied Science and a Master of Physiotherapy Practice from La Trobe University, and a Bachelor of Science from the University of Melbourne. Rebecca has completed further study in women’s health, with a focus on pre- and post-natal conditions. She treats pelvic girdle pain, low back pain and wrist pain, and advises anyone returning to exercise after having a baby. Bec also has a special interest in invisible illnesses including hypermobility, Ehlers-Danlos Syndrome (hEDS), Postural Orthostatic Tachycardia Syndrome (POTS) and chronic fatigue. Outside the clinic, Rebecca plays netball.
This article is general information only and is not a substitute for individual assessment or advice. Please book an appointment so we can tailor recommendations to you. All practitioners at Malvern Physiotherapy Clinic are registered with the Australian Health Practitioner Regulation Agency (AHPRA).
Published February 21, 2024

Managing Common Health Concerns with Physiotherapy Physiotherapy is an essential part of allied health care, offering a hands-on and evidence-based approach to managing a wide range of health...
Learn More
Finding the Best Physiotherapy Near You: A Local Guide If you’ve ever searched “physiotherapy near me” online, you’re not alone. In Australia, thousands of people search this term...
Learn More
By Hayley Runting, Senior Physiotherapist, Malvern Physiotherapy Clinic Common signs of a weak pelvic floor include bladder or bowel leakage, a feeling of heaviness or pressure, and ongoing...
Learn More
Why Real-Time Ultrasound Is a Game-Changer for Muscle and Joint Health Real-Time Ultrasound (RTUS) has emerged as an innovative, highly effective tool in physiotherapy, transforming the way we...
Learn More
Pelvic Floor Muscles – Where are they? What do they do? You may have heard the pelvic floor muscles mentioned in the same sentence as having a baby...
Learn More
For people whose bowels are regular, we don’t give much thought to our poo. However, for those who have challenges – such as diarrhoea, constipation or difficulty controlling...
Learn More
Unfortunately, as we age, we lose muscle mass and strength, impacting our function and quality of life. This condition, known as Sarcopenia, most intensely affects older adults and...
Learn More
Why Bone Health Deserves Your Attention Bone density plays a critical role in long-term health and function — particularly for women. From adolescence through menopause and beyond, a...
Learn More
How Physiotherapy Can Support You Through Pregnancy and Postnatal Recovery Pregnancy is an incredible journey, but it also brings significant changes to your body. As your baby grows,...
Learn More
Understanding Australia’s Most Common Physiotherapy Conditions: What We See Every Day As physiotherapists here at Malvern Physiotherapy Clinic, we’re often asked about the types of conditions we treat...
Learn More
Bladder leakage (urinary incontinence) is not normal. Despite the marketing campaigns from sanitary pad companies, women and men can resolve their urinary leakage in most cases. They do...
Learn More
Good bowel health is an important part of our lives, yet rarely talked about. When discussing this with clients many are surprised at what is considered ‘normal’ for...
Learn More
Have you or someone you know been diagnosed with arthritis? Have you had a scan showing “bone on bone” or been told you’ll inevitably need a joint replacement?...
Learn More
Exercising Safely During Pregnancy: What You Need to Know “In the past, pregnant women were discouraged from exercise. However, this was mainly due to social and cultural biases...
Learn More
Discover everything you need to know about physiotherapy, what physiotherapists do, how they help, and when you should seek advice from a physio. Our warm and friendly team...
Learn More
This blog is the second in a series from Hayley Runting regarding pelvic health conditions. Today’s blog discusses pelvic pain, pelvic surgery and pelvic floor checks. Pelvic Pain...
Learn More
How Can Real-Time Ultrasound Improve Muscle Activation and Recovery? At Malvern Physiotherapy Clinic, we use Real-Time Ultrasound (RTUS) as an assessment and rehabilitation tool to help patients...
Learn More
With all the excitement of having bubs finally at home with the family, mother’s needs are often overlooked. However, this time can be one of the most challenging...
Learn More
As we begin to settle into the new school year, parents have an important role to play in ensuring their children have a healthy, active, and pain-free time...
Learn More
Have you ever had an episode of low back pain? Well, you are not alone! Low back pain (LBP) is a common condition that affects 80% of the...
Learn More
All the joints in the body have the capacity to make noises, some of which are a cause for concern, others are non sinister things happening within the...
Learn More
Chronic Pain and Physiotherapy: What You Need to Know Living with chronic pain can be exhausting. Unlike acute pain, which usually resolves as the body heals, chronic pain...
Learn MoreDiscover everything you need to know about physiotherapy, what physiotherapists do, how they help, and when you should seek advice from a physio. Our warm and friendly team...
Learn More
Sports Injuries: Prevention, Recovery and Performance Sports injuries affect people of all ages, fitness levels, and abilities. While athletes often perform at higher levels of strength and function,...
Learn More
Blood Flow Restriction (BFR) strength training is a new option in rehabilitation for those needing to increase muscle size and strength, and who also need to reduce the...
Learn More
Debunking Myths About Remedial Massage: How It Supports Pain Relief and Recovery Remedial massage is a powerful tool in managing pain, improving movement, and supporting recovery from...
Learn More
To assess, diagnose and manage musculoskeletal conditions Through video-link, your physiotherapist will be able to go through a thorough history of what your complaint is, how it started,...
Learn More
By Mark Fotheringham, Principal Physiotherapist, Malvern Physiotherapy Clinic Shoulder pain from swimming usually comes from load rather than a single injury: doing too much too soon, tired muscles...
Learn More
An ergonomic workspace is important to help maintain good posture while working. When you sit stationary for too long or sit in a slouched position, different muscle groups...
Learn More
The shoulder is one of the most difficult joints to treat as it relies on many components to act in sync for correct function. We as humans are...
Learn More
Winter is here, and with it comes the exhilarating promise of skiing and snowboarding. Whether you’re a seasoned athlete or a family looking forward to your annual ski...
Learn MoreFor people whose bowels are regular, we don’t give much thought to our poo. However, for those who have challenges – such as diarrhoea, constipation or difficulty controlling...
Learn More
Remedial Massage vs Myotherapy: What’s the Difference in Malvern East? If you’re searching for remedial massage in Malvern East or comparing myotherapy in Malvern East, you’re likely...
Learn More